Our philosophy on pain management is simple:
You do not have to suffer.
The physicians and staff at Pain Management Physicians of South Florida understand that each patient has a unique response to pain and it is a philosophy that results in an individual treatment plan.
Our doctors are outstanding diagnosticians who utilize the latest technology and medical advances to treat their patients in a safe, comfortable and relaxing environment.
Our goal is to eliminate the pain generators by identifying those pathologic conditions or triggers that contribute to a painful state. If the pain generators cannot be eradicated, a tailored management plan is introduced to allow patients to take control of their pain.
About Us
Tse C. Lee, MD
Dr. Kavita Sharma, DO
At Pain Management Physicians of South Florida, we recognize that every patient experiences pain differently, so we create personalized treatment plans. Left untreated, pain can disrupt both physical and emotional well-being. Our focus is on identifying and eliminating the sources of pain. If full relief isn’t possible, we develop customized management strategies to help patients regain control over their pain.
Learn More About Our Treatments
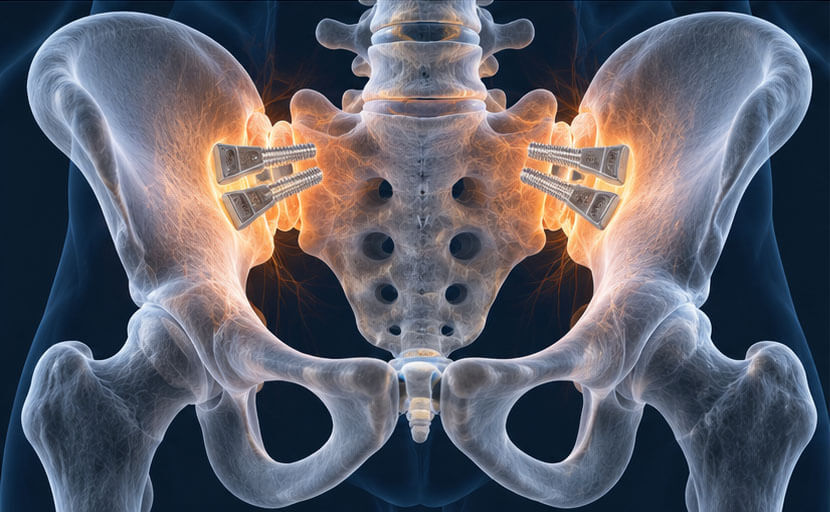
Sacroiliac (SI) joint fusion is a minimally invasive procedure used to stabilize the sacroiliac joint, which connects the pelvis to the lower spine.
For appropriately selected patients with chronic SI joint pain that has not responded adequately to conservative treatments, small implants are placed across the joint to provide stabilization and promote fusion.
The goal of the procedure is to reduce painful movement of the SI joint and improve function.
PRP injections use a concentrated preparation derived from the patient’s own blood and are used as part of a treatment plan for certain musculoskeletal conditions. Available starting October 2026.
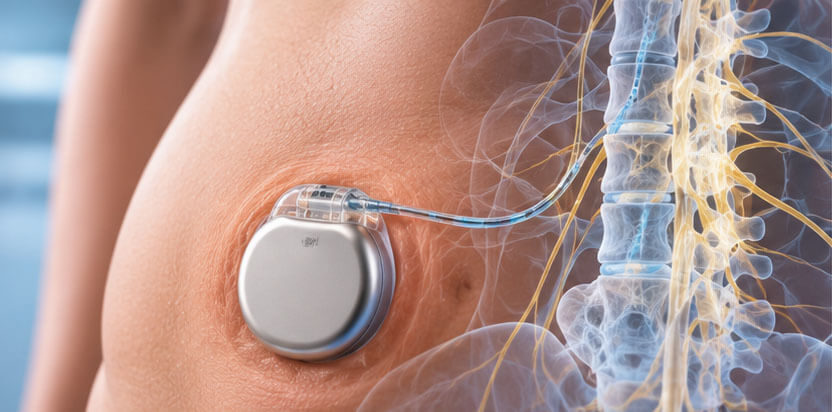
Pain pumps are implantable devices designed to deliver medication directly to the area surrounding the spinal cord. This approach allows medication to be delivered in a controlled manner as part of an individualized treatment plan.
Pain Management Physicians of South Florida provides ongoing pain and baclofen pump maintenance, including medication refills and management, as well as surgical implantation of pain pump systems when appropriate.
Implantable pump therapy may be considered for select patients with chronic pain or spasticity who have not achieved adequate relief with other treatments.
After recovering from COVID-19, a significant proportion of symptomatic and asymptomatic individuals develop Long COVID. Fatigue, orthostatic intolerance, brain fog, anosmia, and ageusia/dysgeusia in Long COVID resemble “sickness behavior,” the autonomic nervous system response to pro-inflammatory cytokines. Aberrant network adaptation to sympathetic/parasympathetic imbalance is expected to produce long-standing dysautonomia. Cervical sympathetic chain activity can be blocked with local anesthetic, allowing the regional autonomic nervous system to “reboot.”
Long COVID patients have been successfully treated using a stellate ganglion block, implicating dysautonomia in the pathophysiology of Long COVID.
Treatments: Stelate Ganglion Blocks
Keywords: Long COVID/PASC, Myalgic encephalitis/chronic fatigue syndrome (ME/CFS), Postural orthostatic tachycardia syndrome (POTS), Dysautonomia, Stellate ganglion block, Cerebral blood flow
Used for muscle tightness and muscle injury in conjunction with a stretching program. Involves the injection of local anesthetic (and/or steroid/Botox) when appropriate.
Back pain effects more than 85% of all Americans during their lifetime. It can have many causes such disc, joint, ligament/bone or muscular pathology. Acute pain (less than six weeks onset) is usually self-limited. Immediate medical attention should be sought when weakness, loss sensation, or bladder/bowel changes accompany the pain. Tumors and malignant causes of pain are rare, occurring in less than 1% of those people suffering from back pain. However, this should be further looked at if neurologic changes occur and the pain doesn’t resolve with treatments. While acute pain is usually recognized as only lasting approximately 6 weeks, chronic pain is generally termed after 12 weeks. Bed rest is not advised, nor is the use of a lumbar support belt for more than two weeks. Most sources of pain respond to conservative treatments, which may include physical therapy, anti-inflammatory medications, topical pain relievers and cortisone injections. Unfortunately, there is a subset of people whose pain is so severe that activities or work are extremely limited during the first six weeks. Or, the pain extends beyond six weeks and approaches the chronic stages of a condition. For these groups of patients, many will respond to interventional pain procedures.
There is no blood test for pain. The diagnosis and treatment require the performance of a careful history and physical exam, along with the use of radiographs (xray, MRI, CT). EMG and nerve conduction studies may also be indicated.
Common causes of back pain include: lumbar disc bulge, lumbar disc herniation, degenerative disc disease, joint inflammation (both facet and sacroiliac), sciatica (pinched nerve), fractures of vertebrae, lumbar spinal stenosis, and prior back surgery (also known as post laminectomy syndrome.
Treatments: Many patients will not respond to the conservative treatments as described above. For those non-responders, interventional pain procedures may be indicated. These interventional treatments, determined by the condition, may include: epidurals, facet blocks, sacroiliac joint injections, MILD procedure, radiofrequency lesioning, neuroplasty/lysis of adhesions, and spinal cord stimulator.
Used to improve mobilization, strengthening and range of motion, mobilization, stabilization and strengthening. Ultrasound, electrical stimulation, ice, heat, bracing and exercise are utilized by trained physical therapists.
Neck pain may not just be limited to the neck but can extend to the head, shoulder and arms. The neck, like the lower back, is composed of many parts, including joints, discs, muscles and nerves. Any of these components can lead to inflammation and pain. For acute pain (less than six weeks onset), most sources of pain respond to conservative treatments, which may include physical therapy, anti-inflammatory medications, topical pain relievers and cortisone injections. Unfortunately, there is a subset of people whose pain is so severe that activities or work are extremely limited during those first six weeks. Or, the pain extends beyond six weeks and approaches the chronic stages of a condition. For these groups of patients, many will respond to interventional pain procedures.
Common causes of neck pain include: spinal stenosis, herniated, disc, degenerative disc, muscle spasms, facet joint disease, whiplash type pain, occipital neuralgia, atlantoaxial joint disease, cervicogenic headaches, and prior neck surgery (also known as post laminectomy syndrome.)
Treatments: Many patients will not respond to the conservative treatments as described above. For those non-responders, interventional pain procedures may be indicated. These interventional treatments, determined by the condition, may include: epidurals, facet blocks, radiofrequency lesioning, atlantoaxial joint injections, and occipital nerve blocks.
Injections of local anesthetic and steroid to target an inflamed spinal nerve or disc under fluoroscopic (x-ray) guidance. Often used for sciatica, pinched nerves, radiculopathy, degenerative disc disease, bulging or herniated discs. Can also be referred to as a nerve block or selective root block. May aid in diagnostic workup or therapeutic treatment. Can be accomplished in the cervical (neck), thoracic (mid back) and the low back (lumbar) segments. May be accomplished with sedation when requested.
Sciatica can be referred to as a pinched nerve. It can be experienced as a radiating leg pain with electric shocks, walking pain, standing pain, or bending over pain.
Common causes of sciatica include disc bulge, disc herniation, ruptured disc, slipped disc, and pinched nerve.
Treatments: For those patients that do not respond to conservative measures, interventional treatments may provide considerable relief. These treatments include transforaminal epidural steroid injections and neuroplasty (lysis of adhesions).
Targeting of the joints and their innervations to help diagnose pain generation from spinal joints in the cervical (neck), thoracic (mid-back), lumbar (low back) segments. This is commonly referred to as mechanical spine pain. Some forms of sciatica and radiculopathy are actually a referred pain from a spinal joint that can mimic a pinched nerve. Accomplished under fluoroscopy (x-ray) and sedation when requested.
Degenerative spine changes occur in most people as they age. For many, the changes do not cause pain. However for some, this can lead to considerable discomfort.
Common causes of degenerative spine pain can be related to spinal bone spurs, degenerative disc disease, spinal stenosis, facet arthritis, arthritic spine. Many people refer to this as walking or standing pain, and discomfort when getting out of bed.
Treatments: Many patients will not respond to the conservative treatments as described above. For those non-responders, interventional pain procedures may be indicated. These interventional treatments, determined by the condition, may include: epidurals, facet blocks, sacroiliac joint injections, MILD procedure, radiofrequency lesioning, neuroplasty/lysis of adhesions and spinal cord stimulator.
Used after a diagnosis of joint pain generators are made for more long-lasting results. Small lesions using radio waves are applied by small needles to destroy pain fibers in the joints of the spine (facets), knees and hips. Fluoroscopic (x-ray) guidance is used with sedation when requested.
Spinal stenosis generally occurs over time and leads to narrowing of bone around the spinal cord or spinal nerve roots. The pain that results from lumbar spinal stenosis may include lower back and leg pain. For the cervical region, the pain may involve both the neck and arm.
A subcategory of spinal stenosis includes neurogenic claudication. This condition leads to pain with walking or standing for no more than 10 minutes. Frequently, patients must sit for a period of time before the pain will resolve. Characteristically, the act of walking in a shopping mall requires frequent breaks of sitting. The act of cooking a meal requires sitting breaks during the food preparation.
Treatments: With the combination of conservative treatments and epidural steroid injections, many patients will have the pain well controlled. For those people that continue to have considerable limitations to walking and standing, options may include spinal surgery or the nonsurgical route of the MILD procedure (minimally invasive lumbar decompression).
This condition is also known as Reflex Sympathetic Dystrophy/Complex Regional Pain Syndrome or sympathetic pain. The discomfort usually involves the arms, hands, legs or feet.
Telltale signs frequently include: sensitivity to touch, swelling, color changes, temperature changes of the painful area.
Successful treatment of this condition is dependent on early recognition and early intervention. Workup is essential and may include but is not limited to radiologic studies and nerve studies.
Treatments: May include therapy and medications. If ongoing pain continues, therapy is not tolerated, or progressively decreasing function of the effected body part is noted, the patient would then be considered for therapeutic sympathetic nerve blocks. Such examples include a stellate ganglion block or lumbar sympathetic block, performed under fluoroscopic guidance. These injections provide treatment for the pain, increased tolerance to physical therapy, and increased function. The use of IV sedation or monitored anesthesia care is frequently provided during these procedures to avoid any discomfort from the procedure itself.
A concentrated dose of local anesthetic and steroid to reduce inflammation within the joint is used for diagnosis and treatment with the aid of fluoroscopy (x-ray).
Facet pain originates at the facet joint. In the cervical spine, one experiences neck pain that can possibly extend to the shoulder, upper arm, head and side of the face. This type of discomfort can be brought on with changes of neck position and may disrupt one’s sleep.
In the lower back, one experiences lower back pain that can possibly extend to the buttock and upper legs. This type of pain is frequently brought on with getting out of bed, get up from a chair, or leaning over. This diagnosis is more dependent upon history and physical exam. Radiologic findings may or may not show any obvious changes at the facet joint.
Treatments: When conservative treatments such as therapy and anti-inflammatory drugs fail to provide relief, fluoroscopic directed injections may provide considerable and long term relief. These injections include diagnostic facet medial branch nerve blocks and more long term approaches via a rhizotomy (also known as radiofrequency lesioning).
Sacral pain can be experienced in the buttock region and can extend to the tailbone, lower back and possibly the upper legs
Common causes of sacral pain include: sacroiliac joint inflammation, and less commonly coccydynia, and sacral fracture. This location of pain can be associated with sitting pain, lying down pain, or pain experienced with crossing the legs.
Treatments: When conservative treatments such as therapy and anti-inflammatory drugs fail to provide relief, fluoroscopic directed injections may provide considerable and long term relief. Such treatments, based upon the cause, may include sacroiliac joint injections, COOLIEF procedures, rhizotomies, or coccyx injections.
Are you suffering from Parosmia, Anosmia, Dysgeusia, or symptoms associated with long COVID? Stellate ganglion blocks may be used as part of a treatment plan for certain patients experiencing these conditions.
At Pain Management Physicians of South Florida, stellate ganglion blocks are performed under fluoroscopic (X-ray) guidance to ensure precise placement.
Stellate ganglion blocks may also be used for the diagnosis and treatment of sympathetic pain conditions affecting the upper extremities, including complex regional pain syndrome (CRPS) and reflex sympathetic dystrophy (RSD). These conditions may occur following trauma or surgery and can cause symptoms such as pain, swelling, changes in skin color or temperature, sensitivity to touch, and changes to the hair or nail beds.
During the procedure, medication is carefully injected near the stellate ganglion, a group of sympathetic nerves located in the neck. The procedure may also be used in the treatment of certain peripheral vascular conditions and Raynaud’s syndrome.
The placement of a needle into the center of a disc to determine whether the disc is a possible pain generator. Procedure is accomplished with x-ray (fluoroscopy) and sedation. Contrast is placed in center of the disc (nucleus) to assess for leaks and pain reproduction as well as measuring the pressures in the disc. Allows for further surgical and non-surgical treatment planning. Used for disc herniation, disc bulge, degenerative disc disease.
The occipital pain is routinely experienced at the base of the skull, It can radiate to the top of the head. In fact, occipital neuralgia can mimic other types of headaches. This problem, may be associated with cervicogenic headaches, and degenerative cervical spine.
Treatments: Coanalgesic medications may help, such as antiseizure medications, antidepressants, muscle relaxants as well as physical therapy.
When this condition persists, the patient may then respond to focus directed injections such as occipital nerve blocks or C2 nerve blocks.
Minimally Invasive Lumbar Decompression (MILD) is a procedure designed to relieve pressure on the spinal nerves in certain patients with lumbar spinal stenosis.
Using a small incision and specialized instruments, the procedure removes small portions of excess ligament tissue that contribute to narrowing of the spinal canal. This creates additional space around the affected nerves without the need for traditional open spine surgery.
MILD may be considered for appropriately selected patients whose symptoms are associated with lumbar spinal stenosis.
Also referred to as midback pain, upper back pain. This condition may or may not be accompanied by pain spreading to the sides or chest.
Common causes may include: degenerative disc disease , thoracic disc herniation, facet joint or vertebral fracture, spinal lesion and spinal stenosis. A comprehensive work up should be included for this type of pain and may include radiologic studies.
Treatments: Based upon the specific cause, treatments may include conservative approaches, spinal injections, kyphoplasty, and possible surgery.
Spinal cord stimulation (SCS) uses electrodes placed near the spinal cord to help block or modify pain signals from the spine and extremities. It may be used in the lumbar (lower back), thoracic (mid-back), and cervical (neck) regions.
Treatment typically begins with a 7-day trial. A small electrode (wire) is placed into the epidural space using an epidural needle and connected to an external power source. The electrode is easily removed at the end of the trial.
If the trial provides meaningful pain relief, the patient may proceed with surgical implantation of a new set of electrodes. Depending on the system being used, treatment may include an implanted generator (similar to a pacemaker battery) or a Bluetooth-enabled system for longer-term therapy.
The system is controlled using a small handheld controller that allows the patient to manage the stimulation.
SCS may be used to treat conditions including post-laminectomy syndrome, failed back syndrome, complex regional pain syndrome (CRPS)/reflex sympathetic dystrophy (RSD), peripheral neuralgia, extremity nerve injuries, and pain associated with peripheral vascular conditions.
For those patients already diagnosed with arthritis of the knee or with ongoing knee pain despite having knee surgery, multiple treatment options have likely already been considered. These treatments may have included therapy, anti-inflammatory agents, cortisone injections, viscosupplementation injections and consideration of a knee replacement.
Treatments: For patients that have failed conservative treatment, are reluctant to undergo surgery, are at high risk for surgery or already failed surgery, they may be a candidate for genicular nerve block and subsequent neurotomy/COOLIEF nerve lesioning.
Conditions: For those patients already diagnosed with arthritis of the hip, multiple treatments options have already been considered. These treatments may have included therapy, anti-inflammatory agents, cortisone injections, viscosupplementation injections and consideration of a hip replacement.
Treatments: This category of treatments apply to those patients who have failed conservative treatment, are reluctant to undergo hip surgery, failed to obtain improvement from hip surgery or are too high of a risk medically to undergo surgery. These patients may be a candidate for a femoral and obturator articular branch nerve block and subsequent neurotomy/COOLIEF nerve lesioning.
Injections on the side of the lumbar spine to assist diagnosis of sympathetic pain issues (complex regional pain syndrome (CRPS) and reflex sympathetic dystrophy (RSD). These injections help lower extremity pain that presents with limb pain, color change, temperature change, swelling, inability to touch the limb, loss of hair and nail bed changes.
They can additionally assist therapeutically and be used in combination with radio frequency lesioning if necessary for longer acting relief. Can occur after surgery or trauma to the limb. Accomplished under x-ray (fluoroscopy) and with sedation. Can additionally be used for peripheral vasculature disease pain.
With this condition, one can experience neck pain with or without shoulder pain, upper arm pain, headaches or facial pain. This type of discomfort can be brought on with changes of neck position and may disrupt one’s sleep.
Radiologic findings may or may not show obvious changes at the facet joint
Treatments: When conservative treatments, such as therapy and anti-inflammatory drugs fail to provide relief, fluoroscopic directed injections may provide considerable and long term relief. Such injections may include facet medial branch nerve blocks and more long term treatments via a rhizotomy.
Groin pain can include discomfort that extends to the lower belly or hips. By the time a patient has made an appointment to see a pain physician, more significant causes such as kidney stones, hernias, or gastrointestinal issues have already been ruled out.
Conditions for groin pain may include hip arthropathy, and post surgical inguinal hernia repair.
Treatments: Based upon the specific cause, treatment options may include selective nerve blocks, nerve ablation procedures and COOLIEF.
This condition may or may not include buttock or leg pain
Sources of this pain may include, spinal stenosis at other levels, facet arthritis, sacroiliac joint inflammation or even scar tissue. Conservative treatments may frequently be dictated by your spine surgeon. If pain persists beyond reasonable expectations, an MRI post surgery will likely be required.
Treatments: Specialized treatments are available for this condition including selective nerve blocks, epidural neuroplasty and even consideration of a spinal cord stimulator trial.
Used for chest wall pain from trauma/rib fracture. Used for diagnostic to distinguish from abdominal issues versus abdominal wall issues. Utilizes fluoroscopy (x-ray) and sedation when requested.
Ongoing pain in the face can be due to numerous conditions. Some of these causes include trigeminal neuralgia, supraorbital neuralgia, infraorbital neuralgia, and temporomandibular joint dysfunction (TMJ). For most people suffering from chronic facial pain, multiple medical specialists have already been consulted.
Treatments: For those people that continue to suffer from considerable pain despite proper treatment, specialized nerve blocks under fluoroscopic guidance may be considered, based upon the diagnosis made.
Nerves such as the ilioingual (groin pain/post hernia surgery), lateral femoral cutaneous nerve (thigh pain), sciatic/piriformis (leg pain), suprascapular block (shoulder). Fluoroscopic (x-ray) guidance utilized along with sedation.
This condition occurs following a painful Shingles outbreak. This type of exquisite pain can be constant, sensitive to touch and travels along the site of the healing rash.
Common locations of this type of pain include the thoracic spine, chest wall, and near the eye and scalp. Initial treatments should include an antiviral medication. Other agents may include topical agents, oral neuropathic medications and possibly analgesics. With the persistence of severe pain, this condition then moves into the chronic stage, known as Post Herpetic Neuralgia.
Treatments: Interventional pain treatments, when performed in these early stages, may break the pain cycle and assist with resolution of the pain syndrome. These include specialized injections called sympathetic blocks, and possibly epidural placed injections.
Injections in the shoulder, hip, knees, wrists, ankles for diagnostic and therapeutic purposes. Can utilize fluoroscopy or ultrasound guidance.